In an operating room, light is not decoration. It directly affects visibility, tissue assessment, and surgical confidence. A narrow beam may illuminate the incision while leaving deep areas in shadow. Glare can also fatigue surgeons during long procedures. These details matter when every movement requires control and attention.
How to choose proper medical lighting for surgeries depends on clinical needs, room design, and staff experience. Surgical lights should provide stable illumination, accurate color rendering, adjustable intensity, and manageable shadows. Their arms must move smoothly without disrupting sterile areas. Handles should support controlled positioning and routine cleaning. Backup power and scheduled maintenance also deserve careful review. A dependable light is part of the safety system, not merely an expensive fixture.
No lamp is perfect. Even advanced equipment may create reflections on instruments or uneven brightness across a deep cavity. This is where practical evaluation becomes valuable. Surgeons, nurses, infection-control teams, and biomedical engineers should assess the light together. They can test it beneath real drapes, around raised hands, and during different procedures. Manufacturer specifications offer useful evidence, but they cannot replace direct observation. A thoughtful choice also considers installation height, heat, energy use, service access, and future replacement costs. Small oversights can become daily frustrations. Careful comparison helps healthcare facilities select lighting that supports clear vision, reliable workflow, and patient-focused surgical care.
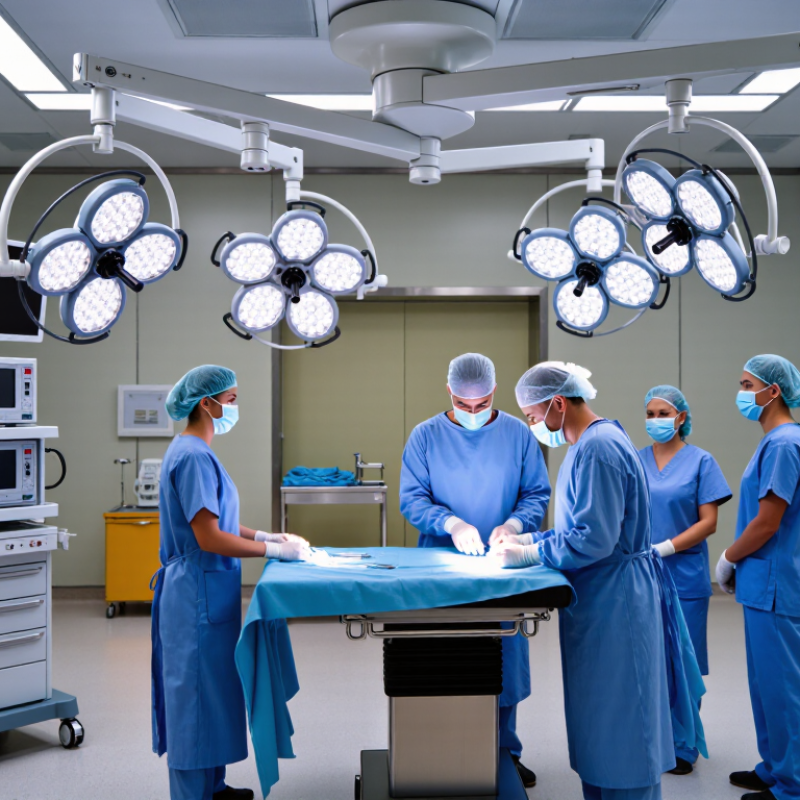
Medical lighting is a specialized system designed to illuminate the surgical field clearly and consistently. It is more than a bright lamp above the operating table. Good lighting supports accurate tissue assessment, controlled movement, and safer decisions during long procedures. It should provide balanced color, adjustable intensity, and strong shadow management. Blood vessels, tissue edges, and small changes in color must remain visible.
Surgeons and nurses often notice lighting problems during demanding moments. A deep cavity may hide detail when the team changes position. Glare can cause eye fatigue. Excessive heat may also affect comfort beneath sterile clothing. Modern surgical lights use focused beams and flexible positioning, but no design solves every situation. Human judgment still matters. Sometimes, a small adjustment works better than maximum brightness.
Tips: Check illumination from the surgeon’s working angle, not only from the room entrance. Test color accuracy with realistic tissue models when possible. Keep handles and controls clean and easy to operate. Ask clinical staff for feedback after procedures. Their practical experience may reveal problems that technical inspections miss. Schedule regular maintenance and verify performance through qualified biomedical personnel. A light can appear functional while producing uneven intensity. That detail is easy to overlook.
In surgery, visibility is not a luxury; it shapes how clinicians interpret tissue, vessels, and wound depth. A well-designed surgical light delivers consistent illumination across the field, even when staff or instruments move. That consistency matters. Poor lighting can create shadows, glare, or washed-out colors, forcing the surgeon to pause or adjust position. Those small interruptions may increase fatigue and complicate precise clinical decisions.
Experienced teams assess more than brightness. They examine color rendering, beam uniformity, focus control, and the light’s response to movement. Natural-looking tissue color supports clearer differentiation between healthy and damaged areas, although lighting alone cannot replace clinical judgment. A practical test is simple: inspect a deep cavity from several angles, with instruments present. Can the team see fine edges without leaning into the field? If not, the setup needs reconsideration. Heat management also deserves attention, because prolonged procedures can make excess warmth uncomfortable beneath protective clothing.
Reliable lighting depends on routine checks, not installation day alone. Staff should verify intensity, positioning, controls, and backup power before each procedure. Cleaning procedures must preserve optical surfaces without damaging them. No light is perfect. Reflections can still appear, and shadows may return during complex movements. Teams should document recurring visibility problems and discuss them during equipment reviews. This approach connects lighting performance with real surgical tasks, staff feedback, and patient safety, while recognizing that human factors remain part of clinical accuracy.
Effective surgical lighting begins with controlled visibility, not impressive brightness. A surgeon needs a clear view of tissue color, depth, and fine edges. High illuminance helps, but excessive brightness can create glare and eye fatigue. Balanced light matters more.
A useful surgical light provides strong color rendering and stable color temperature. These features help distinguish subtle differences between healthy and damaged tissue. Shadow control is equally important. Multiple light sources can reduce shadows from hands, instruments, and the surgeon’s head. Adjustable arms should move smoothly and hold their position without drifting. Sterile handles must be easy to grip and simple to disinfect.
Heat management also deserves attention. A cool light reduces discomfort during long procedures and may improve concentration. Sealed surfaces support cleaning, while smooth joints limit areas where dust can collect. Backup power is valuable when an electrical fault occurs, although it should never replace regular testing. Maintenance teams should record brightness, positioning, battery performance, and calibration results.
In practice, even excellent lighting can fail when positioned poorly. A small blind spot may appear after the table moves. Staff training and room layout therefore matter as much as the fixture itself. I have found that short preoperative checks prevent avoidable adjustments later. Still, no system is perfect. Glare, shadows, or awkward controls may only become obvious during a demanding case, which makes feedback from surgical teams essential.
Choosing medical lighting begins with the procedure, not the fixture. A major operating room needs stable, shadow-reduced illumination across deep cavities. IEC 60601-2-41:2021 specifies central illuminance between 40,000 and 160,000 lux for surgical luminaires. High color rendering also matters. A surgeon must distinguish tissue, blood, sutures, and subtle color changes under pressure.
Different settings require different controls. In a general operating room, choose adjustable intensity, sterile handle access, and a wide field for abdominal procedures. For microsurgery, a focused beam and low-glare optics protect visual concentration. Minor procedure rooms may need around 40,000 to 60,000 lux, plus comfortable ambient lighting for staff movement. Endoscopy rooms need dimmable wall lighting, not complete darkness. That helps nurses read monitors and maintain safe circulation. In intensive care, indirect, low-glare light can support examinations without disturbing resting patients.
Color temperature should match clinical work, often around 4,000–5,000 K. Excessively cool light can feel harsh. Excessively warm light may weaken color judgment. The World Health Organization reports that surgical-site infections affect about 11% of patients in low- and middle-income countries, making reliable clinical conditions essential. Lighting cannot prevent infection alone, yet cleanable surfaces, sealed joints, and documented maintenance reduce avoidable risks. A practical test is simple: place a gloved hand over a wound model and check shadow recovery from several angles. Real rooms reveal problems. Simulations do not. Teams should also review glare, heat, backup power, and staff feedback after installation. Kelvin values alone are not enough.
Surgical lighting safety begins with selecting equipment that meets recognized medical-device standards. IEC 60601-1 addresses essential electrical safety and basic performance. IEC 60601-2-41 applies specifically to surgical and diagnostic luminaires. Hospitals should also check applicable national regulations, electromagnetic compatibility requirements, and documented risk assessments. Compliance is not a decorative certificate. It should match the lamp’s intended operating environment.
Maintenance turns those standards into daily protection. Staff should inspect the light before each procedure. Check brightness controls, movement joints, sterile handles, cables, and backup power indicators. Clean lenses with approved products, because dried disinfectant can scatter light and reduce contrast. Inspect seals for cracks. Moisture can enter unnoticed. Scheduled testing should measure illuminance, color quality, heat output, and electrical leakage according to facility policy and the current service instructions. Calibration records need dates, results, and the responsible technician’s name.
A checklist helps, but it is not perfect. A busy team may sign it without noticing a loose arm or flickering control. Short visual checks should therefore support formal preventive maintenance, not replace it. Any abnormal noise, unstable positioning, sudden dimming, or damaged surface deserves immediate isolation and assessment. Training matters too. Surgeons, nurses, and technicians should know the emergency lighting procedure and report small defects early. Minor faults often become larger safety risks when everyone assumes someone else has noticed.
| Evaluation Dimension | Recommended or Recognized Value | Relevant Standard or Practice | Why It Matters in Surgery | Verification or Maintenance Action |
|---|---|---|---|---|
| Central illuminance | At least 40,000 lux for an operating luminaire; many surgical systems are designed within approximately 40,000–160,000 lux, depending on the operating mode. | IEC 60601-2-41 specifies requirements for operating and diagnostic luminaires. | Adequate light supports tissue differentiation and reduces visual strain without relying on excessive ambient lighting. | Measure illuminance at the specified working distance during commissioning and after major repairs. Use a calibrated lux meter and retain results. |
| Illuminance uniformity | The illuminated field should remain sufficiently even, with no distracting hot spots or abrupt dark areas. Acceptance limits should follow the luminaire specification and applicable standard. | IEC 60601-2-41 test methods and the approved equipment specification. | Uniform lighting helps surgeons maintain visual orientation when the light head or patient position changes. | Check the center and defined points across the light field during preventive maintenance. Investigate uneven output, damaged optics, or contaminated covers. |
| Shadow management | Use a multi-source optical design and verify shadow dilution according to the applicable operating-luminaire test method. | IEC 60601-2-41 includes requirements for shadow dilution and light-field performance. | Multiple light paths reduce shadows caused by the surgeon’s head, hands, instruments, or other equipment. | Perform a functional shadow check after installation, optical repairs, or changes to the operating-room layout. |
| Color temperature | Common surgical-light settings are approximately 3,500–5,000 K; the selected value should support tissue visibility and user preference. | The exact range is generally determined by the equipment design and clinical use rather than by one universal value. | A stable, clinically appropriate color appearance helps distinguish tissue, blood, and materials during procedures. | Confirm the color setting and check for visible color shifts between light sources. Replace aging or mismatched optical modules as specified by the manufacturer. |
| Color rendering | High color rendering is expected for surgical use; many clinical designs target a general color-rendering index around Ra 90 or higher. The approved product specification governs acceptance. | Use the manufacturer’s declared photometric data and applicable medical-luminaire requirements. | Accurate color perception can assist assessment of tissue condition and bleeding. | Check declared values at commissioning and investigate noticeable changes in color appearance or LED-module performance. |
| Heat and infrared control | The light should provide required illuminance while limiting unnecessary radiant heat at the surgical field. Actual limits depend on the applicable standard and equipment design. | IEC 60601-2-41 addresses thermal and photometric performance of operating luminaires. | Reduced heat improves staff comfort and helps limit drying or warming of exposed tissue. | Inspect ventilation paths, heat sinks, protective covers, and cooling systems. Do not operate equipment showing overheating, odor, or abnormal noise. |
| Electrical safety | Protection against electric shock, insulation failure, leakage current, and abnormal operation must be demonstrated. | IEC 60601-1 provides general requirements for basic safety and essential performance. | Surgical staff and patients may be exposed to equipment for long periods in a high-risk environment. | Use qualified biomedical personnel for installation and electrical safety testing. Perform recurrent testing according to IEC 62353, local rules, and the facility risk assessment. |
| Electromagnetic compatibility | The luminaire should operate as intended in the electromagnetic environment of the operating room and should not create unacceptable interference. | IEC 60601-1-2 covers electromagnetic compatibility for medical electrical equipment. | Unexpected flicker, shutdown, or interference can interrupt a procedure and affect other critical equipment. | Check cables, connectors, controls, and nearby equipment after installation or room changes. Follow specified separation distances and installation instructions. |
| Mechanical stability and positioning | The arm, suspension, brake, joints, and light head should hold the selected position without drift, excessive vibration, or uncontrolled movement. | Follow the equipment’s validated mechanical and safety requirements; apply local medical-device maintenance procedures. | Stable positioning prevents accidental contact with the sterile field and maintains consistent illumination. | Inspect joints, handles, covers, fasteners, and brakes at scheduled intervals. Remove from service if the light head droops, swings unexpectedly, or has structural damage. |
| Cleaning and disinfection compatibility | All exposed surfaces should tolerate the cleaning and disinfection agents approved for the facility, without cracking, clouding, corrosion, or loss of markings. | Use the equipment instructions for use, infection-prevention policy, and approved disinfectant compatibility data. | Effective cleaning reduces contamination risk while preserving optical and electrical safety. | Clean between procedures using the approved method. Do not spray directly into vents, joints, switches, or electrical openings. Inspect for residue and surface damage. |
| Controls and backup operation | Intensity controls, focus controls, sterile handles, indicators, and backup functions should operate reliably and be clearly understood by staff. | Essential-performance requirements should be assessed under IEC 60601-1 and the applicable particular standard. | Reliable controls reduce procedure interruptions and allow adjustment without compromising aseptic technique. | Test controls and emergency or backup lighting functions before use and during preventive maintenance. Document failures and corrective actions. |
| Preventive-maintenance frequency | A risk-based schedule is appropriate. Functional checks should be performed before use; formal inspections are commonly scheduled at least annually or more often when risk, usage, or local policy requires. | Facility risk management, local regulations, service documentation, and IEC 62353 testing practices. | Routine checks identify degradation before it affects a procedure or creates a safety hazard. | Maintain service records containing the asset identifier, test date, measured results, defects, technician, corrective action, and next due date. |
| Calibration and measurement traceability | Test instruments such as lux meters and electrical safety analyzers should be suitable for the measurement and within their calibration period. | Apply the facility’s calibration program and documented measurement procedures. | Traceable measurements make it possible to distinguish normal variation from meaningful performance loss. | Record instrument identification and calibration status with each formal test. Repeat measurements when results are inconsistent or outside acceptance limits. |
| Staff training and incident reporting | Users should be trained in positioning, intensity adjustment, cleaning restrictions, fault indicators, and removal-from-service criteria. | Facility medical-device training, incident-reporting procedures, and the equipment instructions for use. | Correct operation reduces misuse, contamination, mechanical damage, and delayed reporting of unsafe conditions. | Provide onboarding and periodic refresher training. Report flicker, overheating, unexpected movement, electrical odor, cracked covers, or repeated faults immediately. |
Note: Numerical values and test intervals should be confirmed against the current edition of the applicable standards, local regulations, the facility risk assessment, and the specific equipment instructions for use. The values above are general technical guidance and do not replace formal acceptance testing.
Clear visibility helps clinicians interpret tissue, vessels, wound depth, and fine edges. Poor lighting may cause shadows, glare, or washed-out colors. Small interruptions can increase fatigue.
No. Excessive brightness can create glare and eye fatigue. Balanced illumination is usually more useful than impressive brightness.
Strong color rendering helps show natural-looking tissue colors. Stable color temperature supports consistent visual interpretation. Lighting cannot replace clinical judgment.
Multiple light sources can limit shadows from hands, instruments, and the surgeon’s head. Staff should inspect deep areas from several angles. Instruments must remain in place during the check.
They should verify intensity, positioning, controls, and backup power. A short preoperative check can prevent later adjustments. It is not foolproof.
Adjustable arms should move smoothly and hold their position. Room layout and table movement can create blind spots. Even good lighting may fail when positioned poorly.
Yes. Excess heat may feel uncomfortable beneath protective clothing. Heat management can support concentration during prolonged procedures.
Staff should clean optical surfaces without damaging them. Maintenance records should include brightness, positioning, battery performance, and calibration results. Regular checks matter.
They should document recurring visibility problems and discuss them during equipment reviews. Staff feedback connects lighting performance with real surgical tasks. Some problems appear only during demanding cases.
Choosing the right medical lighting is essential for creating a safe and effective surgical environment. Medical lighting provides the focused, balanced illumination needed to reveal tissue color, depth, and fine anatomical details while reducing shadows, glare, and visual fatigue. Better visibility supports accurate clinical decisions, precise instrument handling, and consistent performance throughout lengthy procedures. Effective surgical lighting should offer adjustable intensity, reliable color rendering, suitable illumination depth, stable positioning, and easy-to-clean surfaces. It should also minimize heat and remain dependable during demanding operating conditions.
How to choose proper medical lighting for surgeries depends on the procedure, room layout, and clinical workflow. Operating rooms may require powerful, flexible lights, while examination, treatment, or minor procedure areas may benefit from more compact and adaptable systems. Safety also depends on following applicable electrical and medical-device requirements, completing regular inspections, cleaning surfaces correctly, checking movement and controls, and replacing worn components promptly. A thoughtful combination of performance, ergonomics, compatibility, and maintenance can improve surgical visibility while supporting patient safety and staff comfort.

Medivara Medical